Why Hard Training Blocks Wake You at 3am
Quick Answer: Accumulated training stress raises your sympathetic nervous system’s baseline and shifts your cortisol rhythm earlier, so the natural early-morning cortisol rise that should wake you at 6:30 starts firing at 3am instead. Add an elevated core temperature from evening sessions and depleted liver glycogen triggering a small adrenaline release overnight, and you get the classic pattern: exhausted, asleep in seconds, wide awake in the dark. It is one of the earliest and most reliable signals that your training load has outrun your recovery.
The cruel part is that it looks like insomnia and gets treated like insomnia, when it is actually a training-dose problem wearing insomnia’s clothes.
This is general information, not medical advice.


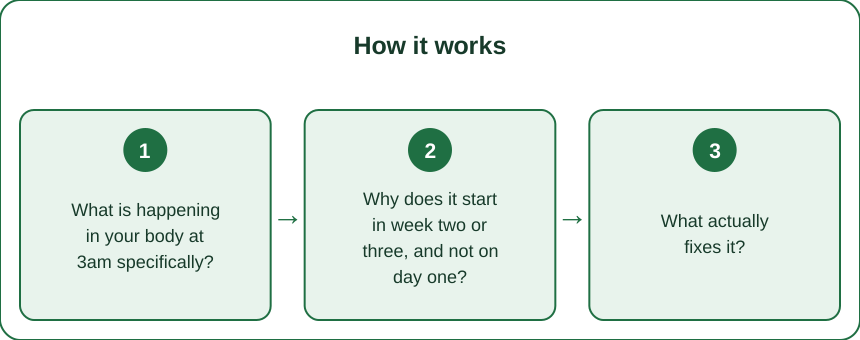
What is happening in your body at 3am specifically?
Three systems collide in the same predawn window.
Your cortisol rhythm has shifted early. Cortisol normally bottoms out around midnight and begins climbing a couple of hours before your usual wake time — it is the body’s natural alarm. Sustained training stress raises the whole curve and drags the rise earlier. The awakening signal that should arrive at 6:30 arrives at 3, and it works exactly as designed: you are awake, and not gently.
Your liver glycogen is low. Hard training days drain liver carbohydrate stores, and the brain guards its overnight glucose supply jealously. When liver glycogen runs thin in the small hours, the body releases adrenaline and cortisol to mobilize backup fuel. That counter-regulatory pulse is enough to snap a light sleeper straight through the surface.
Your baseline arousal is elevated. Weeks of accumulated load raise resting sympathetic tone — slightly higher heart rate, slightly higher core temperature, a nervous system idling fast. Sleep on top of that platform is shallower, and shallow sleep plus a cortisol pulse plus an adrenaline nudge equals eyes open.
The signature that distinguishes this from ordinary insomnia: no racing thoughts at first. You wake alert and physically switched on, and the frustrated thinking arrives second. Stress-insomnia usually runs the other order.
Why does it start in week two or three, and not on day one?
Because a single hard session is an event, and this is an accumulation phenomenon.
One heavy workout produces an acute stress response that your body clears within a day or two — in fact, a lone hard session often deepens that night’s sleep. The 3am pattern emerges when recovery debt compounds: each day you recover slightly less than you spent, nothing feels dramatic, and the ledger quietly grows.
Most people run a structural deficit of a few percent per day during an ambitious block. For the first ten days or so, your reserves absorb it silently. Somewhere in week two or three, the cumulative elevation of stress hormones crosses the threshold where it starts interfering with the systems that were hiding it — and sleep is almost always the first system to show the crack, because sleep architecture is exquisitely sensitive to cortisol and arousal.
This timing is diagnostic gold. Waking at 3am during a taper week or an easy stretch points away from training and toward life stress, alcohol, or something medical. Waking at 3am in week three of a build, after ten days of feeling slightly flat — that is your training talking.
It also explains the tired-but-wired paradox that confuses everyone: fatigue is real (the debt) and the wiredness is real (the elevated stress hormones covering the debt). You are simultaneously overdrawn and running on the overdraft.

What actually fixes it?
Reduce the input, refill the tank, and stop feeding the arousal.
Cut volume, keep moving. The standard response is a deload: roughly 40 to 50 percent less volume for five to seven days, intensity mostly maintained, frequency unchanged. Total rest is rarely needed and often backfires — easy movement helps. A slow evening walk in your most comfortable clothes counts as recovery, not training; treat it that way.
Put carbohydrate at dinner. If your last meal is light on carbs after a heavy day, you are booking the 3am glycogen alarm in advance. A real serving of rice, potatoes, or oats with the evening meal is the single fastest lever for the overnight adrenaline pulse.
Move intensity earlier. Hard sessions within three hours of bed hold core temperature and arousal up past midnight. Shift intervals and heavy lifting to morning or midday during a heavy block; keep evenings for easy work.
Cool the sleep system. A cooler room helps an elevated core temperature fall, and light, breathable sleepwear helps more than people expect — the same buttery-soft fabric you would choose in good leggings beats heavy cotton for overnight temperature regulation.
Cut caffeine at eight to ten hours before bed. Fatigue during a hard block quietly drags caffeine later into the day, and late caffeine amplifies exactly the arousal you are trying to lower.
Most people sleep through the night again within four to seven days of a genuine deload. That response is itself the confirmation of what was wrong.
What Nobody Tells You About Training Sleep Disruption
It mimics insomnia and gets mistreated as insomnia. Sleep hygiene advice — less screens, consistent bedtime — is fine but cannot fix a training-dose problem. If the sleep broke when the block got heavy, the block is the treatment target.
Alcohol makes this specific waking dramatically worse. It sedates you into the first sleep cycles, then its metabolism adds a sympathetic rebound at precisely the hour you were already vulnerable. A drink to knock yourself out is the worst trade available.
Tracking can feed it. Waking at 3am, checking a sleep score, and calculating tomorrow’s readiness raises arousal on the spot. During a heavy block, review sleep data in the morning, never in the night.
It is an earlier signal than your resting heart rate. For many people, the 3am wake shows up days before resting heart rate or heart rate variability move meaningfully. Treat it as the first tripwire, not a curiosity.
Napping is allowed. A 20-minute early-afternoon nap during a deload does not sabotage the night — the prohibition applies to true insomnia, not to recovery debt. Cap it short and keep it before 3pm.
FAQ: Training and 3am Waking, Answered
How many bad nights before I should change something?
Three in one week during a hard block is a pattern, not noise. Act on the pattern — the athletes who wait for two more confirming weeks pay for them.
Should I take melatonin?
It targets falling asleep and circadian timing, not middle-of-the-night waking, so it mostly misses this problem. The dinner-carbohydrate and deload levers act on the actual mechanism.
Can I train through it?
Briefly, knowingly, at declining returns. Planned overreaching does this on purpose for a week or two before a scheduled recovery. Unplanned, open-ended pushing through is how overreaching graduates into genuine overtraining, which costs months.
When is 3am waking not about training?
When it persists through two weeks of real deload, or comes with night sweats, breathing pauses, mood collapse, or it predates the training block. Perimenopause, thyroid issues, sleep apnea, and depression all wake people in the small hours — that cluster belongs with a clinician, not a spreadsheet.
This is general information, not medical advice.
TL;DR:
- Accumulated training load shifts your cortisol rise from 6:30am to 3am and layers an adrenaline pulse from low liver glycogen on top.
- It appears in week two or three of a block because it is compounding debt, not a single-session effect.
- Fixes in order: five-to-seven-day deload, real carbohydrate at dinner, hard sessions earlier in the day, cooler and lighter sleep setup, earlier caffeine cutoff.
- Waking that survives a true deload or comes with other symptoms belongs with a clinician.
If you woke at 3am this week and your training log shows two-plus heavy weeks, run the deload before you buy a single sleep gadget. The log already told you the diagnosis.
This is general information, not medical advice.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
